Physicist Michael Strauss discusses Christianity and science at Stanford university

This is one of my favorite lectures, by one of the people I admire the most for his scientific work and robust, evangelical Christian faith.

About Michael Strauss:

His full biography is here. (I removed his links from my excerpt text below)

Excerpt:

I had an interest in science and theology, so in 1977 I chose to go to Biola University where I could study both subjects in detail. I thoroughly enjoyed college and participated in intramural sports, was elected to student government, served as a resident assistant, competed in forensics, and studied a lot. As I neared college graduation my dual interest continued so I applied to seminary and to graduate school. After graduating summa cum laude from Biola, I decided to pursue a graduate degree in physics at UCLA.

During my first few years of graduate school, I developed an increased interest in quantum mechanics and subatomic physics and decided to do research in a field that dealt with these subjects. I joined a High Energy Physics experimental group doing research at the Stanford Linear Accelerator Center (SLAC) and moved to the San Francisco Bay Area to actively participate in research at SLAC. I graduated in 1988 with my Ph.D in High Energy Physics (a.k.a. Elementary Particle Physics). If you would like to know more about High Energy Physics, the Particle Data Group at Lawrence Berkeley Laboratory has a very nice interactive adventure that teaches you all about the subject. My research advisor was professor Charles Buchanan and my disertation was titled “A Study of Lambda Polarization and Phi Spin Alignment in Electron-Positron Annihilation at 29 GeV as a Probe of Color Field Behavior.”

After graduation, I accepted a post-doctoral research position with the University of Massachusetts at Amherst. I continued to do research at SLAC where I joined the SLD experiment. My research interests centered on the SLD silicon pixel vertex detector. I wrote most of the offline software for this device, and did physics analysis which used the vertex detector, including tagging b quark events for flavor specific QCD (Quantum Chromodynamics) analysis. In the seven years I was employed by UMASS, I only spent 3 days on the Amherst campus. The rest of the time was spent in California.

[…]In August 1995, I accepted a job as an Assistant Professor of Physics at the University of Oklahoma (OU) in Norman, Oklahoma. The University of Oklahoma has a vibrant high energy physics research group involved in experiments at the Fermi National Accelerator Center (Fermilab), and CERN. I joined the DØ experiment at Fermilab where I continue to do research in elementary particle physics. As a member of the DØ collaboration I have made contributions to the testing of silicon sensors for the upgraded vertex detector, to the track finding algorithms, to a measurement of the photon production cross section which probes the gluon content of protons, and to other QCD measurements. I am currently studying properties of B mesons that contain a b-quark, the production cross section of jets coming from quarks and gluons, and other QCD analyses. At CERN, I am a collaborator on the ATLAS detector.

I received tenure in 2001 and was promoted to the rank of Professor in the summer of 2010. Most of the time at OU I have taught introductory physics classes to physics majors, engineers, and life science majors. In these classes I have used a number of interactive techniques to facilitate student participation and learning. I have been privileged to win a few awards for my teaching. In 1999, the Associated Students selected me as the Outstanding Professor in the College of Arts and Science, and in 2000 I was awarded the BP AMOCO Foundation Good Teaching Award. In 2002, I was given the Regents Award for Superior Teaching. I received the Carlisle Mabrey and Lurine Mabrey Presidential Professorship in 2006 which is given to “faculty members who excel in all their professional activities and who relate those activities to the students they teach and mentor.”

He seems to have done a fine job of integrating his faith with a solid career in physics research. It would be nice if we were churning out more like him, but that would require the church to get serious about the integration between science and faith.

The lecture:

Dr. Strauss delivered this lecture at Stanford University in 1999. It is fairly easy to understand, and it even includes useful dating tips, one of which I was able to try out recently at IHOP, and it worked.

You can also listen to the audio here. (MP3)

Summary:

What does science tell us about God?
– the discoveries of Copernicus made humans less significant in the universe
– the discoveries of Darwin should that humans are an accident
– but this all pre-modern science
– what do the latest findings of science say about God?

Evidence #1: the origin of the universe
– the steady state model supports atheism, but was disproved by the latest discoveries
– the oscillating model supports atheism, but was disproved by the latest discoveries
– the big bang model supports theism, and it is supported by multiple recent discoveries
– the quantum gravity model supports atheism, but it pure theory and has never been tested or confirmed by experiment and observation

Evidence #2: the fine-tuning of physical constants for life
– there are over 100 examples of constants that must be selected within a narrow range in order for the universe to support the minimal requirements for life
– example: mass density
– example: strong nuclear force (what he studies)
– example: carbon formation

Evidence #3: the fine-tuning of our planet for habitability
– the type of galaxy and our location in it
– our solar system and our star
– our planet
– our moon

Positive arguments for Christian theism

A closer look at the Christian doctrines of guilt and forgiveness

This is from Randy Alcorn’s Eternal Perspectives web site.

Excerpt:

It is a critical mistake to try to eliminate feelings of guilt without dealing with the root cause of guilt. No matter how often someone says “you have nothing to feel guilty about” to someone who has sinned against God and others, his guilt feelings will remain. Why? Because he knows better. Only by a denial of reality can he avoid guilt feelings. But such a denial is inherently unhealthy. It sets him up for emotional collapse whenever something reminds him of the sin. People need a permanent solution to their guilt problem, a solution based on reality, not denial or pretense.

Because it offers a solution to the guilt problem found nowhere else, I will quote from the Bible and cite references to specific biblical books, chapters and verses. This way you may look up these verses in a Bible yourself and think about them on your own.

Because of Christ’s death on our behalf, forgiveness is available to all.

The word “gospel” means “good news.” The good news is that God loves you, and desires to freely forgive you for all your sins, no matter how ugly or destructive. But before the good news can be appreciated we must know the bad news. The bad news is that there is true moral guilt, that all of us are guilty of many moral offenses against God. “All have sinned and fall short of the glory of God” (Romans 3:23).

The Hebrew word for sin means literally “to miss the mark.” Sin is falling short of God’s holy standards. Sin separates us from a relationship with God (Isaiah 59:2). Sin deceives us and makes us think that wrong is right and right is wrong (Proverbs 14:12). The Bible says, “The wages of sin is death, but the gift of God is eternal life through Jesus Christ our Lord” (Romans 6:23).

Jesus Christ is the Son of God who loved us so much that he became a member of the human race to deliver us from our sin problem (John 3:16). He came to identify with us in our humanity and our weakness, but did so without being tainted by our own sin, self-deception and moral failings (Hebrews 2:17-18; 4:15-16). Jesus died on the cross as the only one worthy to pay the penalty for our sins that was demanded by the holiness of God (2 Corinthians 5:21). Being God, and being all-powerful, he rose from the grave, defeating sin and conquering death (1 Corinthians 15:3-4, 54-57).

When Christ died on the cross for us, he said, “It is finished” (John 19:30). The Greek word (teleo) translated “it is finished” was commonly written across certificates of debt when they were canceled. It meant “Paid in Full.” Christ died so that the certificate of debt consisting of all our sins could once and for all be marked, “Paid in Full.”

Here’s an article from CARM that talks about feeling guilty after getting forgiveness.

Excerpt:

There is an important lesson you need to learn about forgiveness that begins with understanding two things:  justification and sanctification.  Justification is God’s legal declaration upon a sinner in which the sinner is declared righteous in God’s sight; this is also known as salvation.  Sanctification is God working in the Christian, through the Holy Spirit, to make the Christian more like Christ.  Justification is instantaneous; sanctification lasts a lifetime.  Justification is easy because we receive it by faith (Rom. 5:1; Eph. 2:8).  Sanctification is difficult because it is something we do in cooperation with God as He works in our hearts daily.  If we are not very sanctified in our actions, thoughts, and words, we are still justified; we are still saved because of Jesus.  Justification does not depend upon our sanctification.  In other words, our salvation is not dependent on our works in any way.  Justification (salvation) is based upon what Jesus did.  Jesus bore our sins in His body on the cross (1 Pet. 2:24).  Jesus paid for our sins, all of them.  They are gone because He removed them.  It is all because of Jesus and what He did, and not because of what we have done.  Praise be to Him.

Now, I have a question for you.  Can you earn your salvation or do anything at all to merit forgiveness from God?  No, of course not.  That is why salvation is by faith, and not by works or faith and works.  If you did not get your salvation by your works, then you do not keep it by your works, either.  In other words, you do not keep your salvation by doing good or by suffering for your sins so that you might, somehow, be made good enough to be with God.  It can never happen!

Finally, here is the point.  Some Christians, after they have committed a sin, punish themselves by retaining the guilt of their sin and do not receive the full forgiveness of Christ until they have put themselves through enough suffering that they have then “earned” the right to be forgiven.  Of course, this isn’t the intention of holding on to guilt, but sometimes it’s the underlying reason.  It is a danger because it is nothing more than trying to earn the forgiveness of God through our works; in this case, through suffering.  This is an insult to the cross of Christ.

Now, I am not saying that we should never feel guilty for doing something wrong.  I am saying that you should confess your sins and be forgiven (1 John 1:9).  Once confessed and forgiven, it is wrong to harbor the feelings of guilt as a way to punish yourself so that afterwards you might feel you’ve done enough to “feel” good enough to have fellowship with God.  That is what’s wrong, and it is sin.  If that is what you are doing, then you need to realize that God does not require you to pay for your sins through feeling guilty.  He has already paid the full price.  Your part is to humbly and truly confess your sin to the Lord, turn from it, and leave it.  By looking to Jesus and what He has done, you can let the guilt and the guilty feelings fall away from you.  Put your eyes on Jesus.  Praise Him for His great love and forgiveness, and continue in your walk of sanctification.  Lay it all before the cross.

I think the key thing to look for when you are asking for forgiveness is that you have to be sure that what you did really was wrong, based on the Scripture, whether it worked out for you or not. If you do something that the Bible forbids, then there is no excuse for what you did. No desire that you have allows you to sin. No noble purpose you have allows you to sin. No unfair condition allows you to sin. No imagined success or hope of victory allows you to sin. No failure of anyone else allows you to sin. Either you sinned or you didn’t. If you think you didn’t sin then you’re not needing forgiveness, and you don’t have it. If you think you did sin, then you can get forgiveness if you ask Jesus for it, and if you know that he is able to give forgiveness to you.

New survey finds that Canadian health care system quality is declining

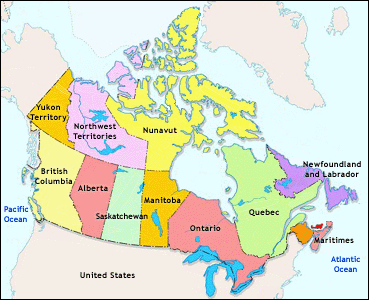
Map of Canada
Map of Canada

A story about a recent survey on Canada’s universal health care system, from the National Post.

Excerpt:

A new survey on attitudes about the health-care system reveals some interesting responses, confirming that Canadians have widespread misgivings about the system, even while not fully understanding how it works. They also favour using tax incentives to encourage healthier living and eating.

The survey of 2,300 Canadians carried out in April by the consulting firm Deloitte was part of a larger poll covering 12 countries. It is considered accurate to within two percentage points, 95% of the time.

Some of the highlights include:

– Just 5% of respondents gave the system an A grade; 45% giving it a B, 36% a C, 10% a D, and 4% a failing F.

– 33% of Canadians said they understood how the system works, down from 39% in 2009 when Deloitte did a similar survey.

– 69% feel that the system has not improved in the last two years, while there were slightly more who thought it had deteriorated, as opposed to improved, in that period.

– 36% believe that half the money spent on health care is wasted; interestingly, half of those skeptics blame the waste on people failing to take responsibility for their own health.

– 13% reported that they are caring for another person, up from 10% in 2009, a possible sign of the increasing personal burden posed by the aging population. In a third of those cases, the individual is caring for a spouse.

– 55% rated their health as excellent or very good … even though 52% report having been diagnosed with one or more chronic diseases.

– 63% favour some kind of tax-based incentive to encourage more healthy diets and lifestyles.

– About 80% favour expanding medical-school enrollments to increase the supply of doctors.

You can find some more videos describing horror stories in the Canadian system in this previous post.

Everyone agrees that the American health care system is too expensive, but do we at least get better quality outcomes? Let’s see.

How good is the American health care system?

Consider this article from the Hoover Institute at Stanford University.

Medical care in the United States is derided as miserable compared to health care systems in the rest of the developed world. Economists, government officials, insurers, and academics beat the drum for a far larger government role in health care. Much of the public assumes that their arguments are sound because the calls for change are so ubiquitous and the topic so complex. Before we turn to government as the solution, however, we should consider some unheralded facts about America’s health care system.

1. Americans have better survival rates than Europeans for common cancers. Breast cancer mortality is 52 percent higher in Germany than in the United States and 88 percent higher in the United Kingdom. Prostate cancer mortality is 604 percent higher in the United Kingdom and 457 percent higher in Norway. The mortality rate for colorectal cancer among British men and women is about 40 percent higher.

2. Americans have lower cancer mortality rates than Canadians. Breast cancer mortality in Canada is 9 percent higher than in the United States, prostate cancer is 184 percent higher, and colon cancer among men is about 10 percent higher.

3. Americans have better access to treatment for chronic diseases than patients in other developed countries. Some 56 percent of Americans who could benefit from statin drugs, which reduce cholesterol and protect against heart disease, are taking them. By comparison, of those patients who could benefit from these drugs, only 36 percent of the Dutch, 29 percent of the Swiss, 26 percent of Germans, 23 percent of Britons, and 17 percent of Italians receive them.

4. Americans have better access to preventive cancer screening than Canadians. Take the proportion of the appropriate-age population groups who have received recommended tests for breast, cervical, prostate, and colon cancer:

  • Nine out of ten middle-aged American women (89 percent) have had a mammogram, compared to fewer than three-fourths of Canadians (72 percent).
  • Nearly all American women (96 percent) have had a Pap smear, compared to fewer than 90 percent of Canadians.
  • More than half of American men (54 percent) have had a prostatespecific antigen (PSA) test, compared to fewer than one in six Canadians (16 percent).
  • Nearly one-third of Americans (30 percent) have had a colonoscopy, compared with fewer than one in twenty Canadians (5 percent).

5. Lower-income Americans are in better health than comparable Canadians. Twice as many American seniors with below-median incomes self-report “excellent” health (11.7 percent) compared to Canadian seniors (5.8 percent). Conversely, white, young Canadian adults with below-median incomes are 20 percent more likely than lower-income Americans to describe their health as “fair or poor.”

6. Americans spend less time waiting for care than patients in Canada and the United Kingdom. Canadian and British patients wait about twice as long—sometimes more than a year—to see a specialist, have elective surgery such as hip replacements, or get radiation treatment for cancer. All told, 827,429 people are waiting for some type of procedure in Canada. In Britain, nearly 1.8 million people are waiting for a hospital admission or outpatient treatment.

7. People in countries with more government control of health care are highly dissatisfied and believe reform is needed. More than 70 percent of German, Canadian, Australian, New Zealand, and British adults say their health system needs either “fundamental change” or “complete rebuilding.”

8. Americans are more satisfied with the care they receive than Canadians. When asked about their own health care instead of the “health care system,” more than half of Americans (51.3 percent) are very satisfied with their health care services, compared with only 41.5 percent of Canadians; a lower proportion of Americans are dissatisfied (6.8 percent) than Canadians (8.5 percent).

9. Americans have better access to important new technologies such as medical imaging than do patients in Canada or Britain. An overwhelming majority of leading American physicians identify computerized tomography (CT) and magnetic resonance imaging (MRI) as the most important medical innovations for improving patient care during the previous decade—even as economists and policy makers unfamiliar with actual medical practice decry these techniques as wasteful. The United States has thirty-four CT scanners per million Americans, compared to twelve in Canada and eight in Britain. The United States has almost twenty-seven MRI machines per million people compared to about six per million in Canada and Britain.

10. Americans are responsible for the vast majority of all health care innovations. The top five U.S. hospitals conduct more clinical trials than all the hospitals in any other developed country. Since the mid- 1970s, the Nobel Prize in medicine or physiology has gone to U.S. residents more often than recipients from all other countries combined. In only five of the past thirty-four years did a scientist living in the United States not win or share in the prize. Most important recent medical innovations were developed in the United States.

Despite serious challenges, such as escalating costs and care for the uninsured, the U.S. health care system compares favorably to those in other developed countries.

The author of that article is a senior fellow at the Hoover Institution and a professor of radiology and chief of neuroradiology at Stanford University Medical School.

So, we saw that the quality of the U.S. health care system is good, but how can we lower the costs? Is government controlled rationing (like Canada) the answer, or is there another way?

Choice and competition in health care

The Center for Freedom and prosperity seems to have found another way: choice and competition.

Excerpt:

In many ways, America’s health care system is the best in the world. It has state-of-the-art technology and highly-skilled medical professionals. America is also home to most of the cutting-edge medical research in the world. However, there are also important problems, such as the “third-party payer” model where consumers rarely pay the full cost of their own health care. This creates an incentive for both excessive and expensive use of health care, a problem that would be exacerbated by current proposals for greater government control of the health care system.

But the third-party payer problem is not the only reason that health care costs are high. State governments impose health insurance coverage mandates, often for “gold-plated” coverage, that drive up the cost of insurance. These regulations, which are unique to each state, are imposed at the behest of interest groups seeking to increase demand for their services. Combined with protectionist barriers that prevent consumers from buying policies from providers in other states, these mandates have severe unintended consequences:

  • They limit competition in the health insurance market by preventing insurance buyers from shopping across state lines, creating monopolistic and oligopolistic situations in many states;
  • They impose coverage mandates that force health insurance buyers to purchase coverage that they either do not want or cannot afford;
  • They force insurers to use community rating instead of experience rating, which means healthy people are forced to subsidize unhealthy people – to the effect that insurance premiums rise for many buyers and healthy people are driven out of the market.

The symptoms of a dysfunctional health insurance market – foremost the significant number of uninsured, but also rising costs – are recognized by many legislators. But the problem cannot be solved, as some suggest, by means of increased government regulation. Indeed, government regulation is the cause of most problems in the health insurance market, not the solution.

Restoring a free market health care system would be a daunting task, one that would involve, 1) sweeping reforms to the 45 percent of health care directly financed by government programs, and 2) a complete rewrite of the tax code to remove the distortions that exist in employer-provided health insurance. This paper focuses on the so-called third leg of the stool – policies to remove government barriers and restore competition to the market for individual health insurance.

Reforming the government-financed programs is definitely necessary because there is so much fraud and waste, as there always is with government, when compared to the private sector. Private sector businesses have to turn a profit, so they actually try to prevent fraud and waste.

Here’s a documentary featuring John Stossel that explains the health insurance problem. (And featuring Regina Hertzlinger, too)

Part 1 of 5:

Part 2 of 5:

Part 3 of 5:

Part 4 of 5:

Part 5 of 5:

Choice and competition govern the way we buy things that we want normally, especially when we buy things online. I am pretty happy buying things from online retailers, because I have so many stores to choose from, with lots of product reviews and retailer ratings. I usually like what I buy, because I know that I am buying a good product from a good seller. And if I don’t get a good outcome, I can leave a review of the product, service or seller as a warning for the next person. That helps to encourage producers to make quality products and services Seller rating helps to make sellers care for customers, and to accept returns on items that don’t perform. Maybe we should do that with health care, and just leave health insurance for catastrophic care – like car insurance is for accidents, but not for oil changes.