
All posts by Wintery Knight

https://winteryknight.com/

How brief was the period in which the Cambrian phyla suddenly appeared?

The Cambrian explosion refers to the sudden appearance of new body plans in the fossil record. ID proponents think that the period is between 5-10 million years at the most. Naturalists want to stretch out the period in which the body plans appear to tens of millions of years. The two sides can’t both be right. What’s the truth?

Evolution News has the answer.

Excerpt:

To establish the length of the most explosive period of innovation within the Cambrian explosion itself, Meyer cites the work of MIT geochronologist Samuel Bowring and his colleagues as well the work of another group led by Smithsonian paleontologist Douglas Erwin. The Bowring-led study showed that (in their words) “the main period of exponential diversification” within the Cambrian lasted “only 5-6 million years” (emphasis added). Meyer explains:

An analysis by MIT geochronologist Samuel Bowring has shown that the main pulse of Cambrian morphological innovation occurred in a sedimentary sequence spanning no more than 6 million years. Yet during this time representatives of at least sixteen completely novel phyla and about thirty classes first appeared in the rock record. In a more recent paper using a slightly different dating scheme, Douglas Erwin and colleagues similarly show that thirteen new phyla appear in a roughly 6-million-year window. (p. 73)

[…][T]ake a look first at the following figure that Bowring and his colleagues included in their definitive 1993 article, published in the journal Science. They use radiometric methods to date the different stages of the Cambrian period, including the crucial Tommotian and Atdabanian stages in which the greatest number of new animal phyla and classes arise. Note that the so-called Manykaian stage of the Cambrian period lasts about 10-14 million years. Note also that the main pulse of morphological innovation didn’t begin during this stage but rather during the Tommotian and Atdabanian — a period that they describe as taking between “5 to 10 million years,” and in a more detailed passage as taking about 5-6 million years.

[…]In the figure above, the Tommotian and Atdabanian stages of the Cambrian period together span only about 5 million years, starting at about 530 and ending about 525 million years ago. Bowring’s figure also depicts the total number of classes and orders present at any given time during the Cambrian period. The biggest increases in morphological innovation occur during the Tommotian and Atdabanian stages. Indeed, during this period the number of known orders nearly quadruples. Moreover, Bowring and his colleagues also make clear that this period corresponds to the main pulse of Cambrian morphological innovation as measured by the number of new phyla and classes that first appear. They note that, while a few groups of animals do arise in the earliest Manykaian stage of the Cambrian, the most rapid period of “exponential increase of diversification,” corresponding to the Tommotian and Atdabanian stages, “lasted only 5 to 6 m.y.”

You can see the figure they are reference in the Evolution News article.

Also, check out these clips that explain the Cambrian explosion:

Part 1:

Part 2:

The first clip features James Valentine, a professor of biology at the University of California who just co-authored a new book on the Cambrian explosion and is not a proponent of intelligent design.

The consensus among scientists regarding the period of time in which the new body plans appear is 5-6 million years. Biologically speaking, that’s a blink of an eye. You aren’t going that kind of complexity and innovation in such a short period of time any more than you can expect to win the lottery by buying 5-6 million tickets when the odds of winning are 1 in a googol (10 to the 100th power – 1, followed by 100 zeroes). You don’t have enough lottery tickets to make winning the lottery likely. Similarly, 5-6 million years is not enough time for naturalistic mechanisms to code brand new body plans from scratch. It would be like trying to research and write a Ph.D thesis during a single lunch hour. It’s just not enough time to produce the amount of information that’s required.
How long do people wait to be treated in a single-payer health care system?

Instead of talking about single payer health care in the abstract (“wouldn’t it be nice if health care were free?”), let’s discuss a concrete case of a single payer health care system. Canada’s health care system is a pure government-funded system.  Canadian residents pay money into the system via taxation. And when they get sick, they go into a government-run hospital and ask for government-run health care. The idea of single payer health care makes a lot of politicians feel good, and it draws applause when they talk about it in the abstract. But forget the abstract. How well does it work in reality?

Here’s an article from a Canadian health care policy expert, Sally C. Pipes.

She writes:

The Canadian single-payer regime subjects thousands of patients to life-threatening delays for treatment.

Our northern neighbors’ wait times grow longer with each passing year. According to the Fraser Institute, a Canadian think tank, the typical patient in need of specialist treatment last year waited 21.2 weeks after referral from a general practitioner — a record high. In 1993, the median wait time was less than half that figure — 9.3 weeks.

In British Columbia, the median wait is even longer — a grand total of 26.5 weeks from referral from a general practitioner to receipt of treatment from a specialist.  That’s more than half a year.

Lengthy delays are a hallmark of single-payer. Demand for care is essentially limitless when someone else is paying the bill.

But the provincial and federal governments in Canada don’t have limitless resources. So they typically set a global budget for care.  Doctors and hospitals can only provide so much care before their costs exceed their revenue from the government. And they can only afford to keep a limited amount of equipment operational, such as MRI machines or CT scanners.

Demand for care inevitably outstrips supply. So the government has to establish wait lists.

Long waits aren’t merely inconvenient; they’re dangerous. Consider the case of Walid Khalfallah, a British Columbian boy with severe scoliosis profiled by the Vancouver Sun in 2012. The Sun reported that he faced a three-year wait for spinal surgery, even though medical guidelines recommended a maximum wait of three months.

Delays can even prove fatal. Long waits have contributed to the deaths of more than 44,000 Canadian women in the past two decades, according to a Fraser Institute study.

Many patients would gladly pay extra to receive care more quickly. But British Columbian law makes it effectively impossible to do so.

The hardest thing to explain to Americans who are only familiar with private insurance is that if the government tells you no in a single-payer system, your only option is to take whatever money you have left (after being taxed for the single-payer system) and go outside the country. A lot of Canadian socialist politicians do exactly that, when they need reliable health care. Like Bernie Sanders, they say one thing to their naive followers, and do something else in their private lives.

So how good is American health care? Maybe Canadians are waiting in line because their health care is so much better than ours.

American health care

One of the best health care policy experts writing today is Avik Roy, who writes for Forbes magazine.

Here is a recent column, which I think is useful for helping us all get better at debating health care policy.

Excerpt:

It’s one of the most oft-repeated justifications for socialized medicine: Americans spend more money than other developed countries on health care, but don’t live as long. If we would just hop on the European health-care bandwagon, we’d live longer and healthier lives. The only problem is it’s not true.

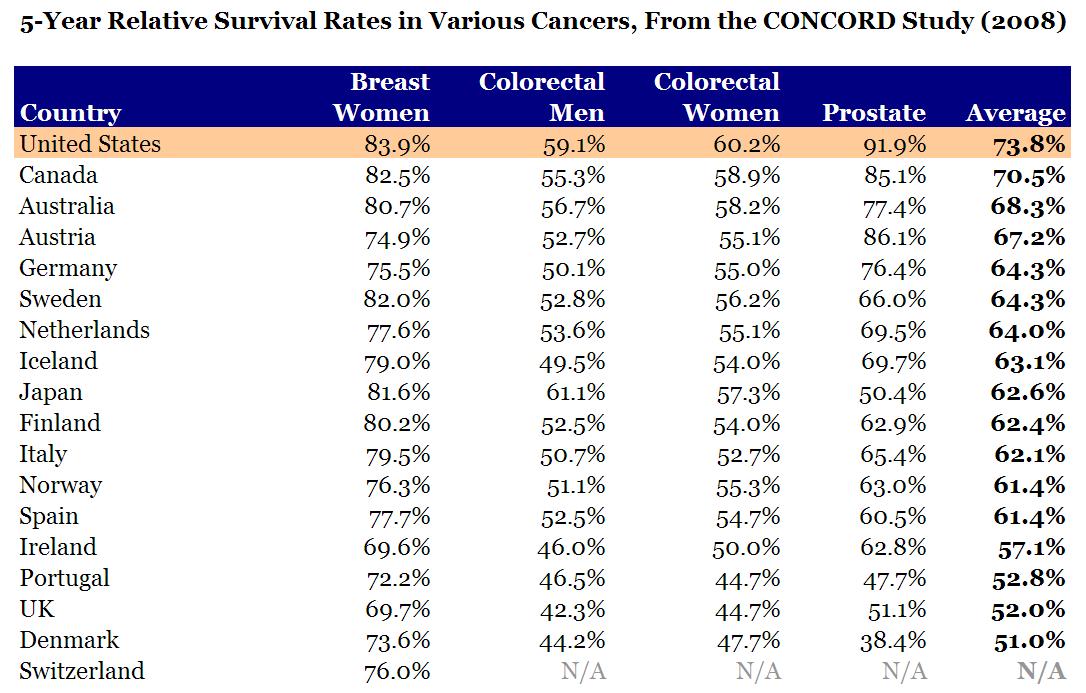
[…]If you really want to measure health outcomes, the best way to do it is at the point of medical intervention. If you have a heart attack, how long do you live in the U.S. vs. another country? If you’re diagnosed with breast cancer? In 2008, a group of investigators conducted a worldwide study of cancer survival rates, called CONCORD. They looked at 5-year survival rates for breast cancer, colon and rectal cancer, and prostate cancer. I compiled their data for the U.S., Canada, Australia, Japan, and western Europe. Guess who came out number one?

Here is the raw data:

Health care outcomes
Health care outcomes by country and type of treatment

Click here to see the larger graph.

So, what explains this?

The article continues:

Another point worth making is that people die for other reasons than health. For example, people die because of car accidents and violent crime. A few years back, Robert Ohsfeldt of Texas A&M and John Schneider of the University of Iowa asked the obvious question: what happens if you remove deaths from fatal injuries from the life expectancy tables? Among the 29 members of the OECD, the U.S. vaults from 19th place to…you guessed it…first. Japan, on the same adjustment, drops from first to ninth.

It’s great that the Japanese eat more sushi than we do, and that they settle their arguments more peaceably. But these things don’t have anything to do with socialized medicine.

Finally, U.S. life-expectancy statistics are skewed by the fact that the U.S. doesn’t have one health-care system, but three: Medicaid, Medicare, and private insurance. (A fourth, the Obamacare exchanges, is supposed to go into effect in 2014.) As I have noted in the past, health outcomes for those on government-sponsored insurance are worse than for those on private insurance.

To my knowledge, no one has attempted to segregate U.S. life-expectancy figures by insurance status. But based on the data we have, it’s highly likely that those on private insurance have the best life expectancy, with Medicare patients in the middle, and the uninsured and Medicaid at the bottom.

Certainly, the life expectancy in our 100% government-run health care system, the Veteran’s Affairs health care system, is really, really low. They just kill the patients, give themselves bonuses, and then cover-up their failures when the investigators come.

I know that my readers who like to dig deep into economics and policy will love the links at the bottom of the article:

For further reading on the topic of life expectancy, here are some recommendations. Harvard economist Greg Mankiw discusses some of the confounding factors with life expectancy statistics, citing this NBER study by June and Dave O’Neill comparing the U.S. and Canada. (Mankiw calls the misuse of U.S. life expectancy stats “schlocky.”) Chicago economist Gary Becker makes note of the CONCORD study in this blog post. In 2009, Sam Preston and Jessica Ho of the University of Pennsylvania published a lengthy analysis of life expectancy statistics, concluding that “the low longevity ranking of the United States is not likely to be a result of a poorly functioning health care system.”

If we’re going to discuss health care, then let’s discuss facts. We shouldn’t be picking a health care system from the campaign speeches of politicians who tell us that we can keep our doctor, and keep our health plan, and our premiums will go down. We tried electing a charismatic deceiver in 2008, and it didn’t work out. We lost our doctors, lost our health plans, and our premiums went up enormously. We can do better than single-payer health care. We can do better than socialism.

Should we expect to know what God’s reason is for allowing evil and suffering?

Lets take a closer look at a puzzle

Here is an article by Steven Cowan about the problems of evil and suffering.

Intro:

The problem of evil is no doubt the most serious challenge to belief in God. Even religious believers find it troubling that evil exists in the world—and so much evil! It is puzzling, to say the least, that an all-powerful, absolutely good being would allow evil to exist in his creation. And yet it does. Evil and suffering exist and they are often overwhelming in their magnitude.

Now let’s find out what a noseeum is, and how it relates to the existence of evil and suffering:

However, perhaps God’s existence is incompatible with a certain kind of evil that exists. For example, the atheist William Rowe has argued that God’s existence is inconsistent with pointless or gratuitous evil. By “pointless evil,” Rowe means evil that does not and cannot serve a greater good. And Rowe believes that there is such pointless evil in the world. He thus concludes that God does not exist. Rowe’s argument may be simply stated as follows:

  1. If God exists, there would be no pointless evil.
  2. There is pointless evil.
  3. Therefore, God does not exist.

[…]But, is there pointless evil in the world? Rowe thinks there is. To show that there is pointless evil, Rowe introduces what he calls the “noseeum inference.” Like the pesty little bugs that some readers may be familiar with, a “noseeum” is something that you cannot see—it is a “no-see-um.” And a noseeum inference is a conclusion drawn on the basis of what one does not see. The basic structure of all noseeum inferences looks like this:

  1. I cannot see an x.
  2. Therefore, there probably is no x.

We all make noseeum inferences everyday of our lives. Every time I go to cross a street, I look both ways and I step out into the street only after I “no-see-um” a car coming.

[…]Rowe applies this kind of noseeum reasoning to God and evil. Rowe suggests that if we cannot see a reason for a particular instance of evil, then there is probably not a reason. Suppose we hear about a very young child who is tortured to death to amuse some psychotic person. We think about this event and we examine all the circumstances surrounding it. No matter how hard we try, we cannot see any good reason why this child had to suffer the way she did. Since we cannot see a reason why God would allow this child to suffer, there probably is not a good reason—the child’s suffering was pointless. Of course, Rowe would be quick to point out that he is not speaking merely hypothetically. There are cases like this in the news every day—real-life cases in which we shake our heads in frustration, wondering why God would allow such a thing.

Is Rowe correct in his conclusion? Do such examples prove that there is pointless evil in the world? I don’t think so. To see why, we must recognize that noseeum inferences are not all created equal. Some noseeum inferences, as we have seen, are reasonable and appropriate. But, many are not. Suppose I look up at the night sky at the star Deneb and I do not see a planet orbiting that star. Would it be reasonable for me to conclude that there is no planet orbiting Deneb? Of course not. Suppose that using the best telescopes and other imaging equipment presently available, I still cannot see a planet around Deneb. I would still be unjustified in concluding that there was no such planet.

In that example, the planet is the noseeum. Just because you look really hard, you can’t be confident that the planet is not there. And similarly with the problem of evil and suffering, looking really hard and finding no reason does not mean that there is no reason. It just means that you are not in a good position to see the reason. You don’t know enough to to be sure that there is no reason, because of your limitations as a human being.

To know that any given instance of evil or suffering is gratuitous/pointless requires a high level of knowledge. How much knowledge? Well, consider this paper by the late William Alston of Syracuse University, who lists six problems with the idea that humans can know that any particular instance of evil and suffering is gratuitous. (You can get the PDF here)

According to the paper, human beings just do not have the capability to know for certain that God has NO morally sufficient reason for allowing any particular instance of evil and/or suffering. God’s morally sufficient reason is a noseeum. To know for sure that there is no reason, we would need to have more knowledge than we do.

Also, remember that on the Christian view, the good aim that God has is NOT to make humans have happy feelings in this life, regardless of their knowledge, wisdom and character. That’s what atheists think, though. They think that God, if he exists, is obligated to make them feel happy all the time. They don’t think that God’s goal is being actively involved in forming their knowledge, wisdom and character. God has a purpose – to work in the world so that everyone who can freely respond to him will respond to him. The Bible says that allowing pain and suffering is one of the ways that he gets that group of people who are willing to respond to respond to him – FREELY. To be able to claim that evil is gratuitous, the atheist has to show that God can achieve his goal of saving all the people he wants to save while permitting less suffering in the world. And that is a very difficult thing for an atheist to show, given our human cognitive limitations.

The best place to learn more about no-see-ums is in this excellent lecture by Biola University professor Doug Geivett.